Opiates and Opioids
No description yet. This curated deck is ready for daily study.
Card preview (24)
Whats the difference between Opiates and Opioids?
Opiates – naturally occurring compounds in the opium poppy that attach to opioid receptors Opioids – Compounds which attach to opioid receptors (includes naturally occurring and (semi)synthetic
What are the sub-categories of Opioids?
• Natural opiates are those in the poppy • Semi-synthetic use poppy opiates as precursors- just have additional groups attached • Synthetic – other molecular precursors; these are very structurally different to the natural opiates
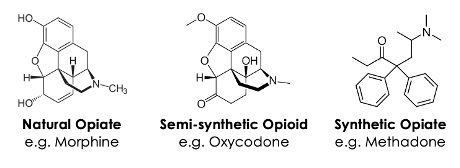
Opioids can be described as being ‘weak’ and ‘strong’, what does this mean?
**‘Weak’ and ‘strong’ **– potency, not concentration (pharmacological affinity and efficacy)

What is the receptor that opioids bind to? What type of receptor is this? What happens when an opioid binds to this receptor?
Gi/o is the protein receptor that opioids bind to A GPCR- inhibits cAMP formation
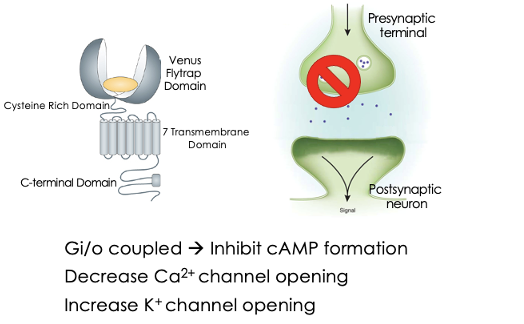
What are the different types of Gi/o receptor for opioids? What are the physiological effects of binding to these receptors?
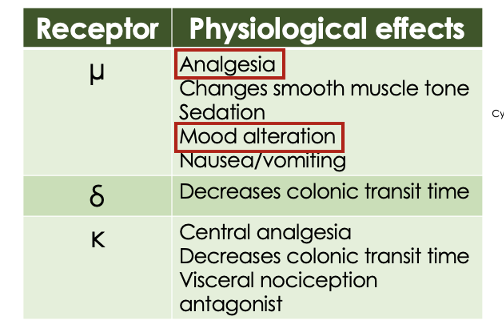
Name some endogenous agonists of opioids? Tell me about them?
Enkephalins and endorphins are opioid receptor agonists, and their activity is very much dependent on receptor mediation • Endorphins thought to mediate response to pain in certain situations. Injection in a dark alley probably hurt more than injection for flu vaccine because endogenous endorphins damped pain response in a ‘flu vaccine’ setting • Endogenous endorphins and enkephalins aren’t as strong as those we can take recreationally
Name some exogenous agonsts of opioids
• Heroin (opiate) • Morphine (opiate) • Codeine (opiate) • Fentanyl (opioid) • Oxycodone • Methadone • …. • Tramadol (also an SSRI, selective serotonin reuptake inhibitor as well an exogenous agonist)
How do users take heroin, what is the most common method and why?
• Can be **smoked or injected ** • Heroin is more commonly smoked than injected. Reasons for smoking • *First time users scared of injecting • *No accessible veins • *Testing a new batch of heroin for potency • Injecting gives a more intense ‘high’
What is heroin methabolised into?
Rapidly metabolised to 6-acetylmornine (6-MAM) and morphine
What is the half life of heroin and 6-MAM?
t1/2 Heroin= 6 minutes t1/2 6-MAM= 30 minutes Hence why in OD you ‘never see heroin’
What are the markers of Heroin
• Heroin markers: 6-MAM, contaminants when opium poppy is grown it is distilled to get the heroin but sometimes there are other opiates present (Noscapine, papaverine, thebaine)
How can one tell if overdose is due to Heroin, Morphine or codeine?
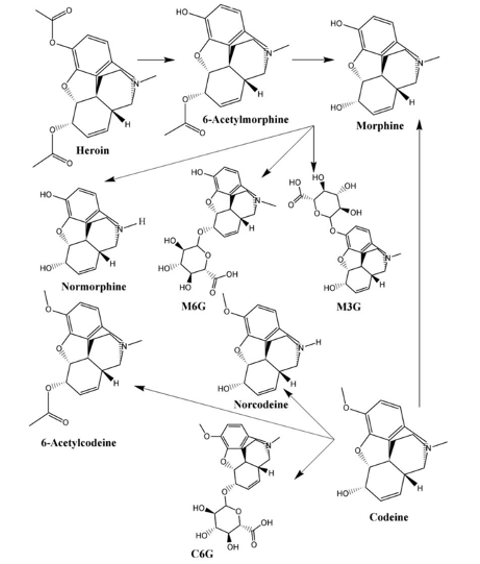
• Heroin markers: • 6-MAM present (therapeutic and illicit) • Contaminants present (Noscapine, papaverine, thebaine) (illicit) • Morphine • Metabolised to other components (morphine-3-glucuronide and morphine-6-glucuronide) • No 6-MAM present in morphine OD so use this to distinguish if used has taken heroin or morphine • No contaminants • Codeine • Converted to morphine via enzyme (this enzyme is variable and can effect rate of conversion) • Codeine is an opioid but not as potent as morphine, high analgesic effect if have fast metaboliser for codeine • No 6-MAM • morphine ≤ Codeine (as codeine is metabolised to morphine so morphine will be present if codeine taken but at a lower amount)
What are the fentanyls?
• Fentanyl 50-100x more potent than morphine • Carfentanyl 10,000x more potent • Carfentanyl marketed as Wildnil for darting rhinos etc. • Use to adulterate heroin, make it ‘stronger’ • Even having carfentanyl in the air can be fatal
What are the pharmaceutical fentanyls?
Fentanyl, remifentanyl, sufentanyl, alfentanyl
What are the non-pharmaceutical fentanyl derivatives (NPFDs)?
Carfentanyl, ocfentanyl, butyrylfentanyl
Deaths with the fentanyls
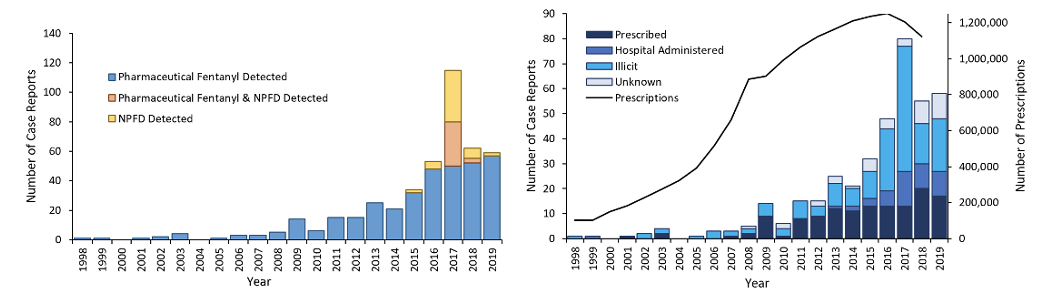
• Massive spike in 2017 when pharmaceutical fentanyl was detected with NPFD, and this came from heroin that was mixed with carfentanyl. This lab supplying this shut down which lessened the rate and the people who took that drug and had heard about deaths didn’t want to use the drug (LHS graph) • Just deaths with fentanyl shows illicitly precured fentanyl. Problem with prescriptions being misused and those illicitly sourcing for recreational purposes. (RHS graph)
What are the desirable effects wanted from opioids?
o Analgesia o Cough suppression (methadone can be prescribed in people with lung cancer as good cough suppressant and pain relief) o Euphoria- big reason why used recreationally o *Antidiarrheal action
What are the unwanted effects from opioids?
o Respiratory depression o Nausea/vomiting o Pupillary constriction o Dependence o Histamine release- causes user to scratch them self in withdrawal as causes mast cell degeneration/degranulation in periphery and releases histamine which causes skin itching Non-drowsy (allergy) and drowsy (crosses BBB, if take with heroin then will inhibit mast cell degranulation, and will provide some sedation, but can cause loss of consciousness, respiratory depression and death) o *Antidiarrheal action
Tell me about the oxycontin crisis?
• Aggressive marketing campaign –> Targeted doctors who had large chronic pain patient rosters • ‘Risk of addiction is less than 1%*’- what doctors were told when being marketed Oxycontin, however was addictive o The study where this 1% figure was from was about burns patients who received limited doses • Increased dependence with this in the US in particular “paving the way for the current fentanyl crisis”- >90% of deaths in <50 due to fentanyl
Tell me about the cycle of addiction with opioids?
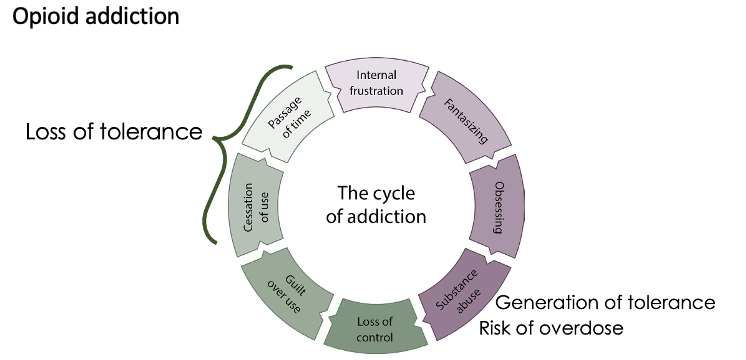
• Tolerance: if taken drug your body adapts, and you don’t feel the same effects so take a higher dose. These keeps occurring until there’s a cross over between therapeutic effects wanted and respiratory depression • If relapse and start to use at same level which you stop using, then could be a fatal dose as you have lost the tolerance you initially had
What are the treatments for opioid addiction and an example one for each?
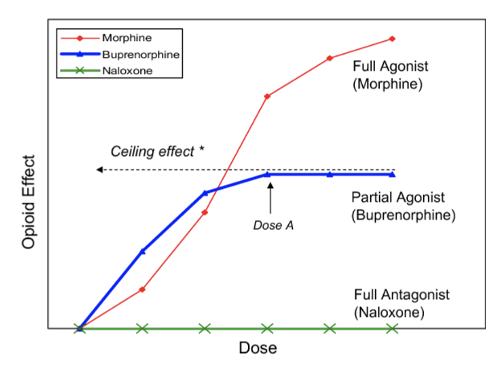
* Antagonists o Naloxone- high affinity for opioid receptor, competitively antagonise and stops opioids binding, this is quick o Naltrexone * Opioid substitution therapy- chronic users o Methadone- full agonist but not as potent o Buprenorphine- High affinity, low efficacy
There is currently a study looking into the administration of naloxone via drone
• Can die very quickly so getting naloxone to people quickly is key to save lives • Doing a case in Plymouth
Tell me about naloxone half life
* Case scenario: o Heroin user reports to A&E o Classic signs of opioid toxicity o What are they? Losing consciousness Struggling to breath Pupillary effect o Given naloxone o Woke up and became agitated o Restrained and put in cubicle o Seemed to settle (no more shouting, not ‘seen’ for an hour) o Found lifeless o Why? Naloxone has a short half-life So reversed that part of opioid experience So naloxone has been metabolised and could be high opioid levels in body • Half-life of naloxone 1-1.5hrs. Heroin 4-6 hours. Naloxone can be metabolised whilst still in the window for heroin overdose
Tell me about methadone
• Still an opioid (i.e., addictive) • ‘Weaker’ than heroin • Long duration of action (24-36hrs vs 4-6hrs for heroin) • No euphoria • Daily supervised dosing (then take home)- do daily supervised before take home to ensure they aren’t supplying or taking more than recommended dose